

Indian Journal of Health Social Work
(UGC CARE List Journal)
THE EFFECTS OF ALCOHOL AND CANNABIS ON
NEUROCOGNITIVE FUNCTIONS
Vandana Kaushik1, Nandha Kumara Pujam. S2
1Clinical Psychologist in Private Practice, New Delhi., 2Associate Director & Associate Professor
of Clinical Psychology, Rashtriya Raksha University (An Institution of National Importance),
Shivamogga Campus, Shivamogga, Karnataka
Correspondence: Nandha Kumara Pujam s., e-mail: nandhakumara2008@gmail.com
ABSTRACT
Clinical evidence observed that the long-term use of cannabis may lead to cognitive impairment
in the higher cognitive functions. Additionally, research has revealed the presence of neurocognitive
deficits in chronic heavy alcohol users. The present study aimed to compare the deficit in executive
function and memory in patients with alcohol and cannabis dependence syndrome. Method: The
present study is a cross-sectional design conducted at Shree Guru Gobind Singh Tricentenary
(SGT) Hospital, Gurugram, Haryana. 30 patients with alcohol dependence and another 30 patients
with cannabis dependence were selected using the purposive sampling method. To measure
memory and executive function, the Wisconsin Card Sorting Test, the Stroop Colour Word Test,
and the PGI Memory Scale were administered to all 60 participants. Results: There is a significant
difference in attention and concentration, non-perseverative errors and percent non-perseverative
errors and Stroop word between cannabis and alcohol dependence patients. Conclusion: The
present study confirms the pivotal role of executive function deficit in patients with alcohol and
cannabis dependence syndrome.
Keywords: alcohol, cannabis, stroop, WCST, memory scale, executive function.
Submitted: 29.01.2026 Revised: 27.03.2026 Accepted: 03.06.2026 Published: 30.07.2026
How to cite this article: Kaushik, V. & Pujam,N.K.S. (2026). The Effects of Alcohol and
Cannabis On Neurocognitive Functions. Indian Journal of Health Social Work, 8(1), 79-83.
INTRODUCTION
Clinical evidence indicates that the long-term
use of cannabis may produce cognitive
impairment in the higher cognitive functions
of memory, attention, and organization, as
well as in the integration of complex
information (Sadock, et al., 2015). Previous
studies have reported cognitive deficits in
alcohol dependence patients, which include
short-term memory deficits (Knight &
Longmore 1994) and executive function
deficits (Noel et al. 2001). Tamm et al. (2013)
examined 42 cannabis users and reported that
i ndividuals who began using cannabis
regularly before age 16 may have poorer executive functioning than users who began
later. Indlekofer et al. (2009) examined the
cognitive functioning of 284 participants with
alcohol and cannabis. Participants were
administered neuropsychological tests which
consists of memory, executive function test
(WCST and Stroop test) and observed poor
executive function. Chronic heavy users of
alcohol (Bsates & Bowden, 2002) have shown
neurocognitive deficits in earlier research.
Furthermore, studies indicate that the early
onset cannabis users exhibit poorer cognitive
performance than late-onset users (Pope et
al. 2001). Furthermore, there is a deficit in
attention, concentration, memory and
executive functions in individuals with alcohol
and cannabis dependence (Solowij et al.,
2011). There is a dearth of studies on adult
cannabis and alcohol dependence, and to
overcome the limitations of existing literature,
the present study is an attempt to identify the
difference in cognitive deficits between alcohol
and cannabis dependence, which further
contributes to a better treatment plan
METHODOLOGY
Sample
The present study is a cross-sectional design
conducted at Shree Guru Gobind Singh
Tricentenary (SGT) Hospital, Gurugram,
Haryana. 30 patients with alcohol dependence
and another 30 patients with cannabis
dependence were selected using the
purposive sampling method. The present study
aimed to compare the executive function and
memory in patients with alcohol and cannabis
dependence syndrome. With the inclusion
criteria of AUDIT and CUIDT scores of 8 and
above. The diagnosis of alcohol and cannabis
dependence was made according to the ICD
10 DCR criteria. The study hypothesised that
there will be no significant difference in
executive function and memory in patients
with alcohol and cannabis dependence
syndrome.
Tools Used
The Alcohol Use Disorder Identification Test
(AUDIT) (Saunders et al., 1993) is a 10-item
screening tool developed by the World Health
Organization (WHO) to assess alcohol
consumption, drinking behaviours, and
alcohol-related problems. The cannabis use
disorder identification test (Adamson et al.,
2010), CUDIT-R, is a 10-item self-report
questionnaire to classify individuals with
cannabis-related problems. The Wisconsin
Card Sorting Test (Heaton, 1981) is a test to
assess abstract reasoning ability and the
ability to shift cognitive strategies in response
to changing environmental contingencies. The
Stroop Colour-Word Test (Golden, 2002)
measures the relative speed of reading words,
naming colours, and identifying the colours
used to print an incongruous colour name. The
stroop test has traditionally been viewed as a
measure of executive functioning in response
inhibition. The PGI Memory Scale (Prasad and
Wig, 1977), or PGIMS, includes verbal and
non-verbal material and measures remote,
recent, and immediate short-term, very short
term, intermediate-term, and long-term
memories.
Procedure
After getting permission from the Institutional
Ethics Committee. Those patients who fulfilled
the inclusion and exclusion criteria were
selected for the study. Written informed
consent was taken from the patient after
explaining the objectives of the study. Those
who scored 8 and above in AUDIT and CUDIT
were administered the PGI Memory Scale,
Stroop Colour Word Test and Wisconsin Card
Sorting Test. Data was analysed using the
Statistical Package for the Social Sciences
(SPSS) version 16.0. Descriptive statistics
were analysed for socio-demographic
variables. To identify the difference in
executive function and memory between the
cannabis and alcohol groups, an independent sample ‘t’ test was analysed.
RESULTS
Table-1: Socio-demographic
characteristics of the cannabis and
alcohol dependence patients.
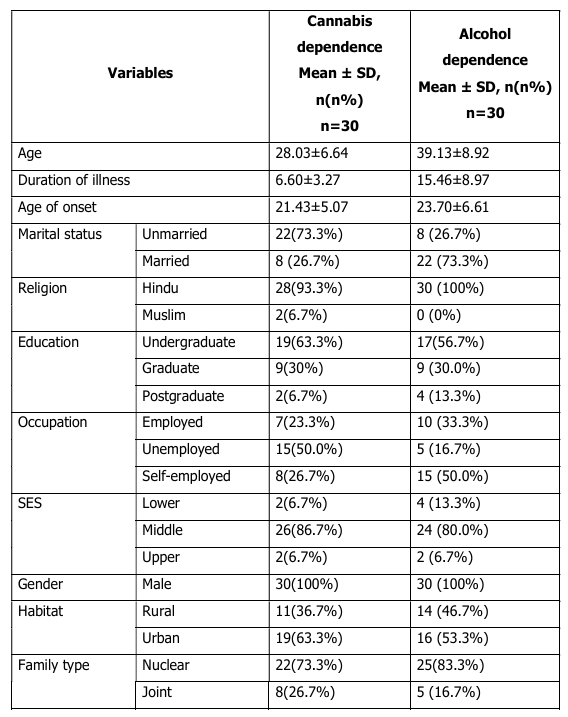
Table-1: Shows the descriptive statistics of
sociodemographic variables. The mean age
of the alcohol group was higher than the
cannabis group. The alcohol group had a
longer illness duration and older onset age
than the cannabis group. The groups had more
unmarried patients. The cannabis group had
more undergraduates than the alcohol group.
Most of the alcohol and cannabis group were
part of the nuclear family type. Similarly, most
of the alcohol and cannabis group were from
urban backgrounds.
Table-2 Comparisons of memory
functions between cannabis and alcohol
dependence patients.
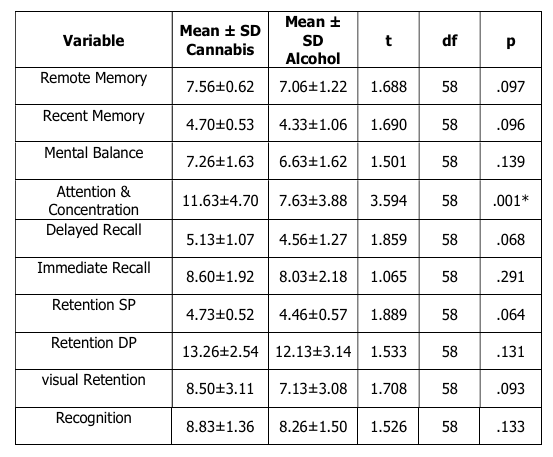
Table-2: Shows the comparisons of memory
functions between cannabis and alcohol
dependence patients using an independent
sample t-test. There is a significant difference
between cannabis and alcohol dependence
patients in attention and concentration (p <
.001).
Table-3: Comparison of WCST scores
between cannabis and alcohol
dependence Patients.
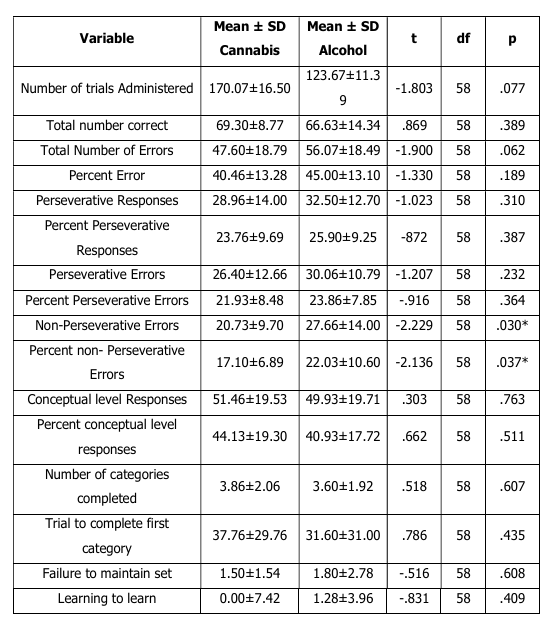
Table-3: Shows the comparison of WCST
scores between cannabis and alcohol
dependence patients using an independent
sample “t” test. There is a significant difference between cannabis and alcohol
dependence patients in non-perseverative
errors and percent non-perseverative errors
(p<.05).
Table-4: Comparison of Stroop scores
between cannabis and alcohol
dependence patients.
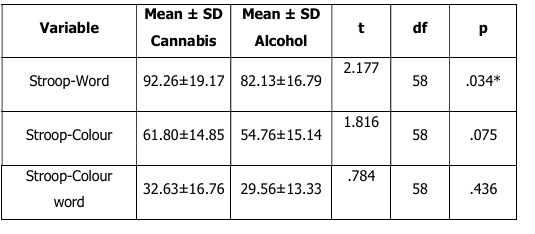
Table-4: Shows the comparison of Stroop
scores between cannabis and alcohol
dependence patients using an independent
sample “t” test. There is a significant
difference between the cannabis and alcohol
dependence patients in the Stroop word
(p<.05).
DISCUSSION
The present study reported there is a
significant difference between cannabis- and
alcohol-dependent patients in attention and
concentration. This indicates the cannabis
group showed better attention and
concentration than the alcohol patients. This
finding is in support of the earlier study by
Loeber et al. (2009), which evaluated 15
patients with longer durations of alcohol
dependence and 15 patients with shorter
durations using the d2 test of attention and
reported a significant difference in attention
and concentration. In contrast, sustained
attention, measured with continuous
performance tasks, is inconsistently impaired
in chronic cannabis users (Pope et al., 2001;
Indlekofer et al., 2009). In a study by Solowij
et al. (2002) that evaluated 51 long-term
cannabis users and 51 short-term cannabis
users, they reported that long-term heavy
cannabis users show impairments in memory
and attention. There is a significant difference
in non-perseverative errors between patients
with cannabis dependence and those with
alcohol dependence. Tarter (1973) examined
chronic alcoholics using the WCST and found
that long-term alcoholics required more trials
and made more errors; they also experienced
greater difficulty in abandoning previous
concepts and cognitive sets.
CONCLUSION
The present study confirms the crucial role
of executive function deficits in patients with
alcohol and cannabis dependence syndromes.
Relatively small size and excluding female
participants are a few limitations of the study.
REFERENCES
Adamson, S. J., Kay-Lambkin, F. J., Baker, A.
L., Lewin, T. J., Thornton, L., Kelly, B.
J., Sellman, J. D. (2010). An improved
brief measure of cannabis misuse: The
Cannabis Use Disorders Identification
Test-Revised. Drug and Alcohol
Dependence, 110(1), 137-143.
Golden, Z. L., & Golden, C. J. (2002). Patterns
of performance on the stroop color
and word test in children with
Learning, Attentional, and Psychiatric
Disabilities. Psychology in school
39(5), 489-495.
Heaton, R. K. (1981). A manual for the
Wisconsin Card Sorting Test, Odessa,
FL: Psychological Assessment
Resources.
Indlekofer, F., Piechatzek, M., Daamen, M.,
Glasmacher, C., Lieb, R., Pfister, H., …
& Schütz, C. G. (2009). Reduced
memory and attention performance in
a population-based sample of young
adults with a moderate lifetime use
of
cannabis,
ecstasy
and
alcohol. Journal of psycho
Knight, R. G., & Longmore, B. E. (1994). Brain damage, behavior and cognition:
developments
i n
neuropsychology.
clinical
Clinical
neuropsychology of alcoholism.
Hillsdale, NJ, US: Lawrence Erbaum
Associates, Inc.
Noel, X., Van der Linden, M., Schmidt, N.,
Sferrazza, R., Hanak, C., Le Bon, O.,
De Mol, J., Kornreich, C., Pele, Pelc,
I., Verbanck, P. (2001). Supervisory
attentional system in non-amnesic
alcoholic men, Archives of General
Psychiatry, 58(12), 1152-1158.
Pope, H. G., Gruber, A. J., Hudson, J. I.,
Huestis, M. A., & Yurgelun-Todd, D.
(2001).
Neuropsychological
performance in long-term cannabis
users. Archives
of
general
psychiatry, 58(10), 909-915.
Sadock, J. B. James, B., Sadock, V. A., (2015)
Kaplan & Sadock’s Synopsis of
Psychiatry: behavioral Sciences/
Clinical Psychiatry, 11th Edition.
Saunders, J. B., Aasland, O. G., Babor, T. F.,
de la Fuente, Jr., & Grant, M. (1993).
Development of the Alcohol Use
Disorders Identification Test: WHO
Collaborative project on early
detection of person with harmful
alcohol consumption- II. Addiction,
88(6), 791-804.
Solowij, N., Jones, K. A., Rozman, M. E.,
Davis, S. M., Ciarrochi, J., Heaven, P.
C. L., Lubman, D. I. & Yucel, M.
(2011). Verbal learning and memory
in adolescent cannabis users, alcohol
users
and
non-users.
Psychopharmacology, 216 (1), 131
144.
Solowij, N., Stephens, R. S., Roffman, R. A.,
Babor, T., Kadden, R., Miller, M., … &
Vendetti, J. (2002). Cognitive
functioning of long-term heavy
cannabis
users
seeking
treatment. Jama, 287(9), 1123-1131.
Conflict of interest: None
Role of funding source: None
